Oxygen
General advice:
-
Oxygen is a treatment for hypoxemia not breathlessness
-
Must be prescribed on drug chart according to target saturations
-
Target sats 88-92% initially, if history of moderate or severe COPD, hypercapnia or previous NIV
-
Nasal prongs give following approximate inspired 02 concentrations 1L/min = 24%; 2L/min = 28% but use should be considered in type 2 respiratory failure where there is a need for controlled oxygen.
-
Perform ABG if oxygen required to achieve sats >88%
Type I respiratory failure (Pa02 low, PaCO2 normal/low)
Type II respiratory failure (Pa02 low, PaCO2 high)
-
Target sats 88-92%
-
Start with low concentration 02 i.e. 24 – 28% by Venturi mask
-
Nebulisers should be air driven and any necessary oxygen administered simultaneously via nasal cannulae for duration of nebuliser
-
Measure arterial blood gases 30 minutes after any change in 02 concentration
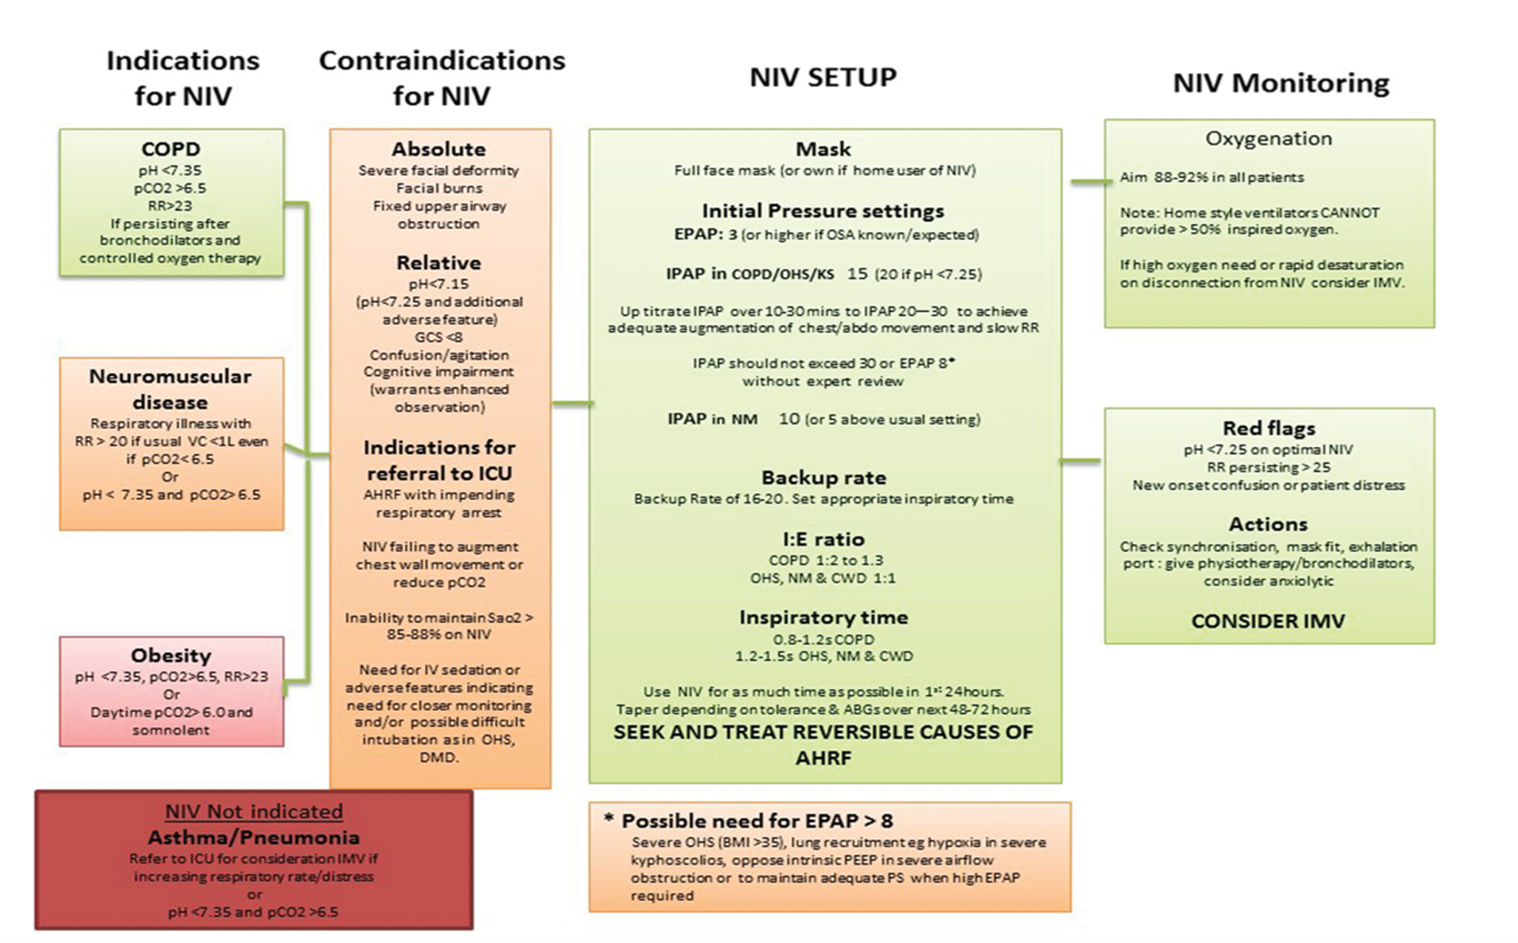
Consider NIV if acidosis persists after initial standard medical therapy or in extremis. Consider ceiling of treatment early.
Antibiotics
- Indicated if sputum more purulent or CXR suggestive of pneumonia
- Obtain appropriate cultures first - i.e. blood cultures
- Do not delay antibiotic therapy because awaiting results or sputum sample. Refer to antibiotic policy on intranet for empirical treatment Antimicrobial prescribing policy microguide.global
- Sputum cultures should be performed if purulent sputum present
Other agents
-
Nebulised beta agonists - Salbutamol 2.5 - 5 mg
-
Continue inhaled triple therapy where possibleSteroids prednisolone 30mg od for 5-7 days
-
VTE prophylaxis as per trust guidelines
If not settling, consider
If not settling – consider: