Key Points
-
The Clinic Letter stating the procedure and the relevant imaging should be reviewed at the time of consent and marking
-
Patient’s should be marked with a blue or black skin marker either on the ward or in the procedure room prior to the WHO “Time Out”
-
Combinations or text and arrows are all acceptable providing the following rules are followed
-
The patient should be marked on the same side as the planned injection
Combination injections should be marked in such a way that the correct side and level of the procedure can be easily determined from the skin marking alone
Marking should be visible during sterile prep and in the surgical field if draping
This is a controlled document. If you are using a printed copy, check it against the guidelines site to ensure you are using the latest edition. Print copies must be destroyed after use.
Abbreviations
Best Practice
-
The clinic letter stating the procedure and relevant imaging should be reviewed at the time of consent and marking.
-
Patients should be marked with a blue or black skin marker. This can be done either on the ward or in the procedure room prior to the WHO “Time Out”
-
Relevant Imaging and the last clinic letter should be displayed during the “Time Out” with the clinician confirming that this matches the consent form.
-
Combinations of arrows and text are all acceptable providing the following rules are followed.
This guideline is applicable to the following procedures (cervical, thoracic and lumbar):
-
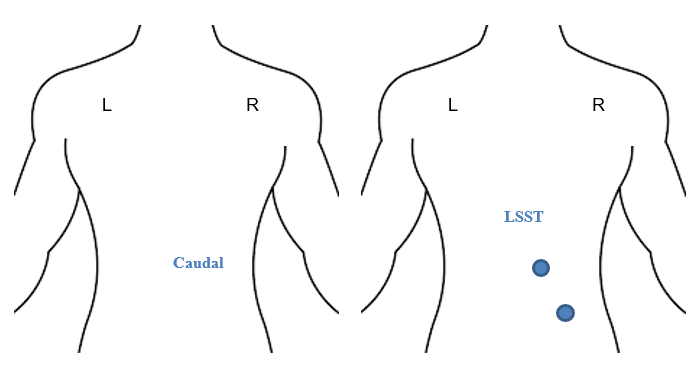
Caudal Epidural
-
Foraminal Epidural
-
Nerve Root Block
-
Medial Branch Block
-
Facet Joint Injection
-
Dorsal Root Ganglion Blocks
-
Radiofrequency Denervation
-
Lumbosacral Screen and Treat
-
Interlaminar Epidural
NOTE: This is a Guideline only and the diagrams below are examples only and ultimately common sense should be used to try and avoid wrong site injections
Rule 1
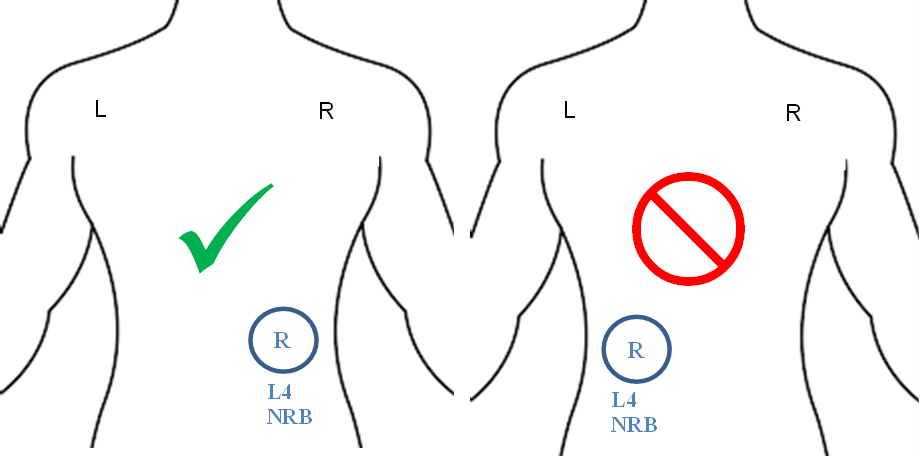
- The patient should be marked on same side as the planned injection.
eg. Right L4 Nerve Root Block
Rule 2
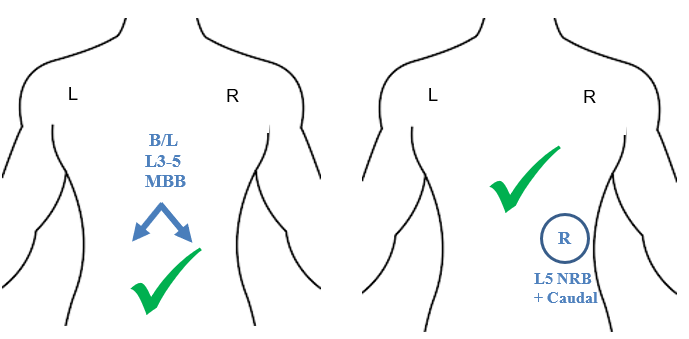
- Combination injections should be marked in such a way that the correct side and level of the procedure to be performed can be easily determined from the skin marking alone.
Eg. Bilateral L3-L5 Medial Branch Blocks Eg. Right L5 NRB + Caudal Epidural
Eg. Right L1/2 and Left L4/5 Foraminal Epidural
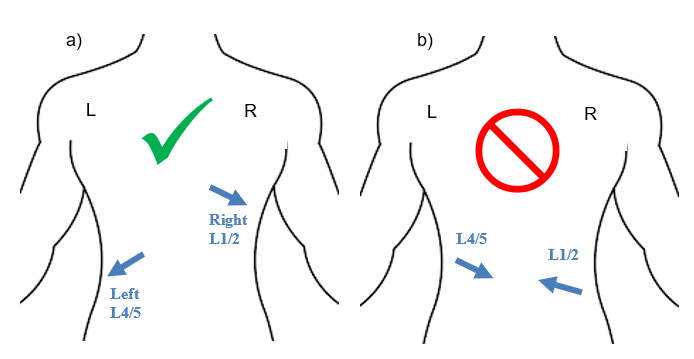
Note: In this above example, the arrows which point towards the midline in diagram b) could be misinterpreted and thus it is recommended that if using arrows for marking that these point away from the midline towards the correct side and be accompanied with a Left(L) or Right(R). In this example the marking is at a very similar level and thus it is also recommended that the marking be anatomically correct.
Rule 4
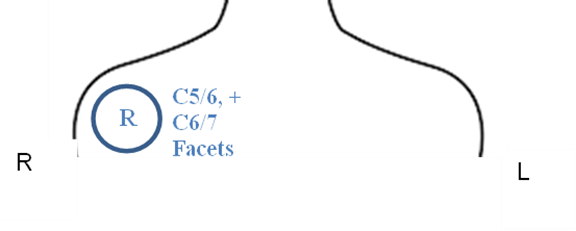
- The marking should be visible during sterile prep and visible in the surgical field if draping. For example if a cervical injection is to be performed in the supine position then this should be clearly visible on the upper chest. It is recommended that unless a cervical procedure is to be performed in the prone position then the marking should be performed anteriorly.
Eg Right C5/6 + C6/7 Facet Joint Injections