Key Points
This is a controlled document. If you are using a printed copy, check it against the guidelines site to ensure you are using the latest edition. Print copies must be destroyed after use.
Abbreviations
Secondary metastases are more common that primary brain tumours. Tumour types which more commonly result in brain metastases are lung, breast, melanoma, renal and colorectal cancer.
FHFT AOS team support primary brain cancer patients in FPH and WPH until they have had a diagnosis and MDT discussion in St George’s Hospital (SGH) Neuro-oncology MDT or Oxford University Hospital (OUH) Neuro-oncology MDT. Please refer primary brain cancer patients to AOS via Epic if inpatient or via email if discharged home.
Common Presenting symptoms Include:
-
Headache, nausea and vomiting.
-
Confusion, seizures.
-
Neurological deficit (for example speech disturbances, limb weakness, ataxia, may be progressive over days to weeks).
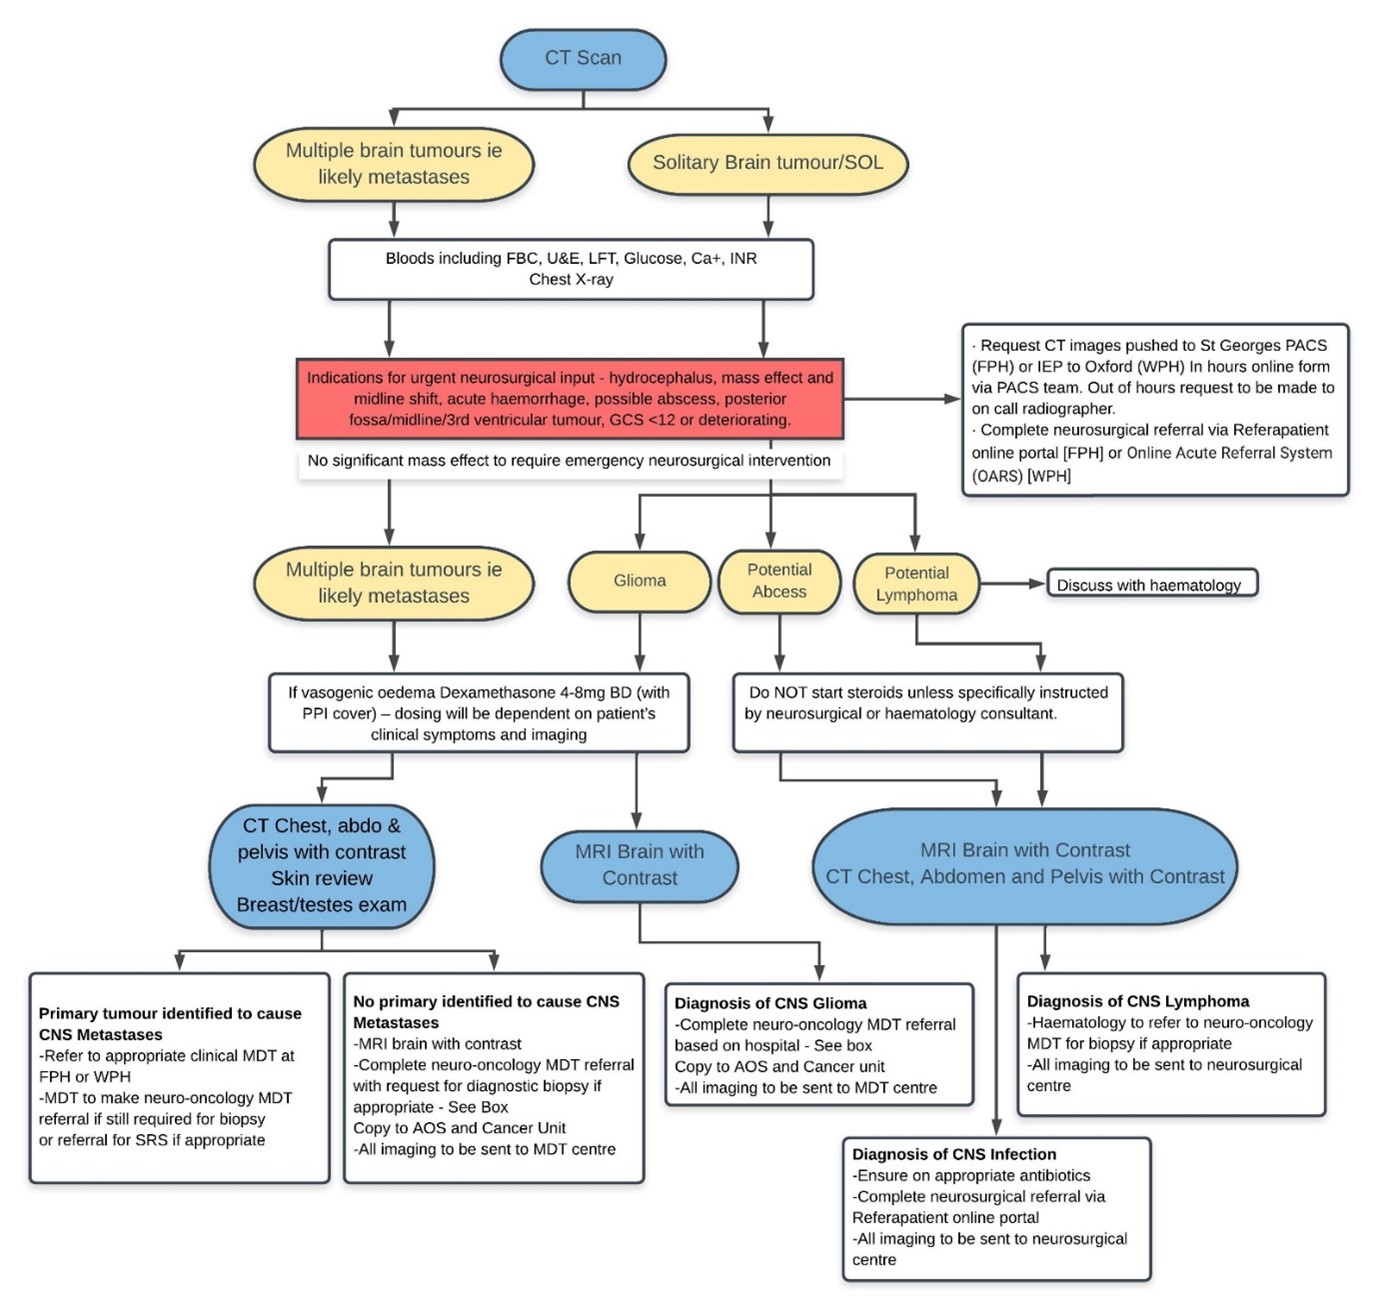
CT reports an intrinsic tumour likely glioma. No significant mass effect to require emergency neurosurgical intervention.
-
Request inpatient MRI with contrast. If no diagnostic uncertainty of glioma does not require staging CT.
-
If associated vasogenic oedema start dexamethasone 4-8mg bd with PPI cover for 1 week
-
MRI confirms intrinsic glioma complete neuro-oncology MDT referral (deadline is SGH MDT Wednesday at 10am and for OUH MDT Friday 12:00) and copy to
fph-tr.cancerunitfph@nhs.net (FPH) and fhft.aoscnsfph@nhs.net (FPH) or
fph-tr.mdtcoordinatorswx@nhs.net (WPH) and fhft.aoscnswph@nhs.net (WPH)
-
Request CT and MRI images pushed to St Georges PACS, or Oxford In hours online form via PACS team.
Make sure GP letter includes details of potential diagnosis.
CT reports an intrinsic tumour likely glioma/metastasis. Significant mass effect to require emergency neurosurgical intervention.
-
Request CT images pushed to St Georges PACS or sent via IEP to Oxford. In hours online form via PACS team. Out of hours request to be made to on call radiographer.
-
Complete neurosurgical referral via Referapatient online portal
-
If not for emergency transfer under neurosurgery request inpatient MRI with contrast
-
If associated vasogenic oedema start dexamethasone 8mg bd with PPI cover for 1 week
-
MRI confirms intrinsic glioma inform neurosurgical on-call and complete neuro-oncology MDT referral (deadline for SGH MDT is Wednesday at 10am and OUH MDT is Friday 12:00) and copy to fph-tr.cancerunitfph@nhs.net (FPH) and fhft.aoscnsfph@nhs.net (FPH) or fph-tr.mdtcoordinatorswx@nhs.net (WPH) and fhft.aoscnswph@nhs.net (WPH)
-
Request outstanding CT and MRI images pushed to St Georges PACS. In hours online form via PACS team. Out of hours request to be made to on call radiographer.
Make sure GP letter includes details of potential diagnosis.
CT reports metastatic disease. No significant mass effect to require emergency neurosurgical intervention.
-
If no primary cancer diagnosis known CT Chest, abdomen and Pelvis with contrast. May also require skin examination, breast examination, endoscopy etc based on CT results.
-
If associated vasogenic oedema start dexamethasone 4-8mg bd with PPI cover for 1 week
-
If primary tumour identified resulting in brain metastases, patient to be referred and discussed at local MDT
-
Multiple small metastases through the brain should not go to the neurosurgical MDT.
-
If local cancer MDT/oncologist think the patient is clinically suitable for treatment and they meet the commissioning criteria for radiosurgery, they should make a referral to the Royal Marsden Stereotactic Radiosurgery (SRS) MDT or Oxford Neuro-oncology MDT.
-
If no primary tumour identified request inpatient MRI with contrast
-
If requires biopsy of brain metastasis for histology diagnosis make referral to neuro-oncology MDT (deadline is SGH MDT Wednesday at 10am and for OUH MDT Friday 12:00) and copy to fph-tr.cancerunitfph@nhs.net (FPH) and fhft.aoscnsfph@nhs.net (FPH) or fph-tr.mdtcoordinatorswx@nhs.net (WPH) and fhft.aoscnswph@nhs.net (WPH)
-
Request CT and MRI images pushed to St Georges PACS or IEP Oxford In hours online form via PACS team.
Make sure GP letter includes details of potential diagnosis.
CT or MRI reports possible CNS lymphoma. No significant mass effect to require emergency neurosurgical intervention.
-
Do NOT start steroids unless specifically instructed by neurosurgical or haematology consultant.
-
Discuss with haematology team
-
Request MRI brain with contrast and also staging CT neck, chest, abdomen and pelvis with contrast
-
When all imaging acquired complete neuro-oncology MDT referral (deadline for SGH MDT is Wednesday at 10am and OUH MDT is Friday 12:00) and copy to fph-tr.cancerunitfph@nhs.net or fph-tr.mdtcoordinatorswx@nhs.net in conjunction with haematology team for planning of biopsy
ED/Medical teams roles and responsibilities:
-
Roles and responsibilities IEP images and phoning neurosurgeons (if required)
-
Complete neuro-oncology MDT referral
-
Inform patient (and AOS) of potential diagnosis and explain not allowed to drive (DVLA notification)
-
TTO dexamethasone and PPI
-
Arrange contrast MRI
-
To exclude metastases or cancer below the neck please order CT CAP, perform breast / testicular exam any lumps
-
Ensure discharge letter to GP explains the above
AOS/Cancer unit roles and responsibilities:
-
Give patient brain tumour Macmillan booklet if suspected malignancy (Mon- Sun 8am-4pm)
-
Follow up patient 48hrs post for dexamethasone dose reduction.
-
Chase scans / ensure images are pushed via PACS for MDT
-
Get result of St George’s Friday MDT, or Oxford’s Tuesday MDT and co-ordinating appropriate follow up
-
Inform patient of next steps
Contact details and tertiary centre links:
Full version control record
This guideline has been registered with the Trust. However, clinical guidelines are guidelines only. The interpretation and application of clinical guidelines will remain the responsibility of the individual clinician. If in doubt, contact a senior colleague or expert. Caution is advised when using guidelines after the review date.
This guideline is for use in Frimley Health NHS Foundation Trust hospitals only. Any use outside this location will not be supported by the Trust and will be at the risk of the individual using it.
Version History
Related Documents