Key Points
-
Antenatal Hydronephrosis is dilatation of the renal collecting system.
-
It can be diagnosed by ultrasound, and it is classified as mild, moderate or severe, depending on the measurements of the anterior posterior diameter of the renal pelvis.
-
In case of mild hydronephrosis a follow up scan should be booked at 32 weeks for further review.
-
Referral to Fetal Medicine Unit is indicated in case of moderate or severe hydronephrosis, or if there are any additional findings on the ultrasound scan.
-
Mode and timing of delivery is not affected by antenatal hydronephrosis.
-
All cases of bilateral or severe unilateral dilatation should be discussed with the duty neonatal consultant prior to discharge.
-
All cases of unilateral severe or bilateral moderate hydronephrosis, should have antibiotic treatment postnatally.
-
Further imaging and follow up appointment should be arranged postnatally by the neonatal team, upon discharge from the hospital.
This is a controlled document. If you are using a printed copy, check it against the guidelines site to ensure you are using the latest edition. Print copies must be destroyed after use.
Abbreviations
1. Purpose
This guideline will ensure that the maternity service has systems in place for appropriate management when renal pelvic dilatation (interchangeably used with antenatal hydronephrosis) is detected on antenatal ultrasound, and guidance for staff on management of such events.
2. Background
Antenatal hydronephrosis (ANH) refers to renal collecting system dilatation, regardless of its aetiology. Pyelectasis indicates dilatation of the renal pelvis and caliectasis indicates dilatation of renal calyces.
The early demonstration of antenatal hydronephrosis has several benefits: the preservation of the renal function, the prevention of urinary infections and the treatment of urinary tract obstructions.
Fetal hydronephrosis is the most common anomaly detected on antenatal ultrasound examination, and its significance and management remain controversial. The incidence of ANH varies somewhat according to the definition of hydronephrosis adopted and is around 1 in 500.
The risk of significant urological pathology increases with the severity of prenatal hydronephrosis.
4. Rationale for ultrasound screening
-
High-resolution 2D ultrasound allows detailed assessment of the kidney from the second trimester of pregnancy.
-
ANH can represent a number of renal pathologies, the most common being:
-
Uretero-pelvic junction obstruction (UPJO)
-
Vesico–ureteric reflux (VUR)
-
Posterior urethral valves (PUV) and
-
Uretero–vesical junction obstruction (UVJO)
-
Duplex kidney
-
A number of other renal anomalies may also be detected, including cystic disease, renal dysplasia, single kidney, etc
-
Abnormalities of other organ systems may sometimes coexist with renal anomalies.
5. Detection of antenatal hydronephrosis
Accurate measurement of the size of the renal pelvis is crucial in assessment and it is imperative that appropriate images are taken and the dimensions measured. The maximum diameter of the renal pelvis in the transverse plane (APD) is the crucial measurement. Once hydronephrosis has been identified further assessment includes review of the amniotic fluid, bladder (volume, bladder wall thickness, emptying), appearance of the ureters and assessment of the kidneys (position, size, texture, renal pelvis AP diameter).
6. Classification of antenatal hydronephrosis (ANH) by anterior posterior diameter (APD)
 by anterior posterior diameter (APD).JPG)
Presence of any of the features below will grade the hydronephrosis as ‘moderate’ to ‘severe’ regardless of the renal pelvis measurement and will warrant referral to Fetal Medicine Unit.
7. Antenatal management
-
Detection in Second Trimester
-
If hydronephrosis (APD≥7mm) is detected, the woman should have a follow up scan in the main ultrasound department at 32 weeks for further review. An information leaflet should be given at this stage.
-
If severe hydronephrosis (APD≥10mm) is detected, the woman should be referred to Fetal Medicine Unit for review in the next 7-14 days. Follow up scan should be arranged every 4 weeks or sooner if indicated. Referral to a tertiary centre if the fetal medicine team feels this is required (Appendix 1).
-
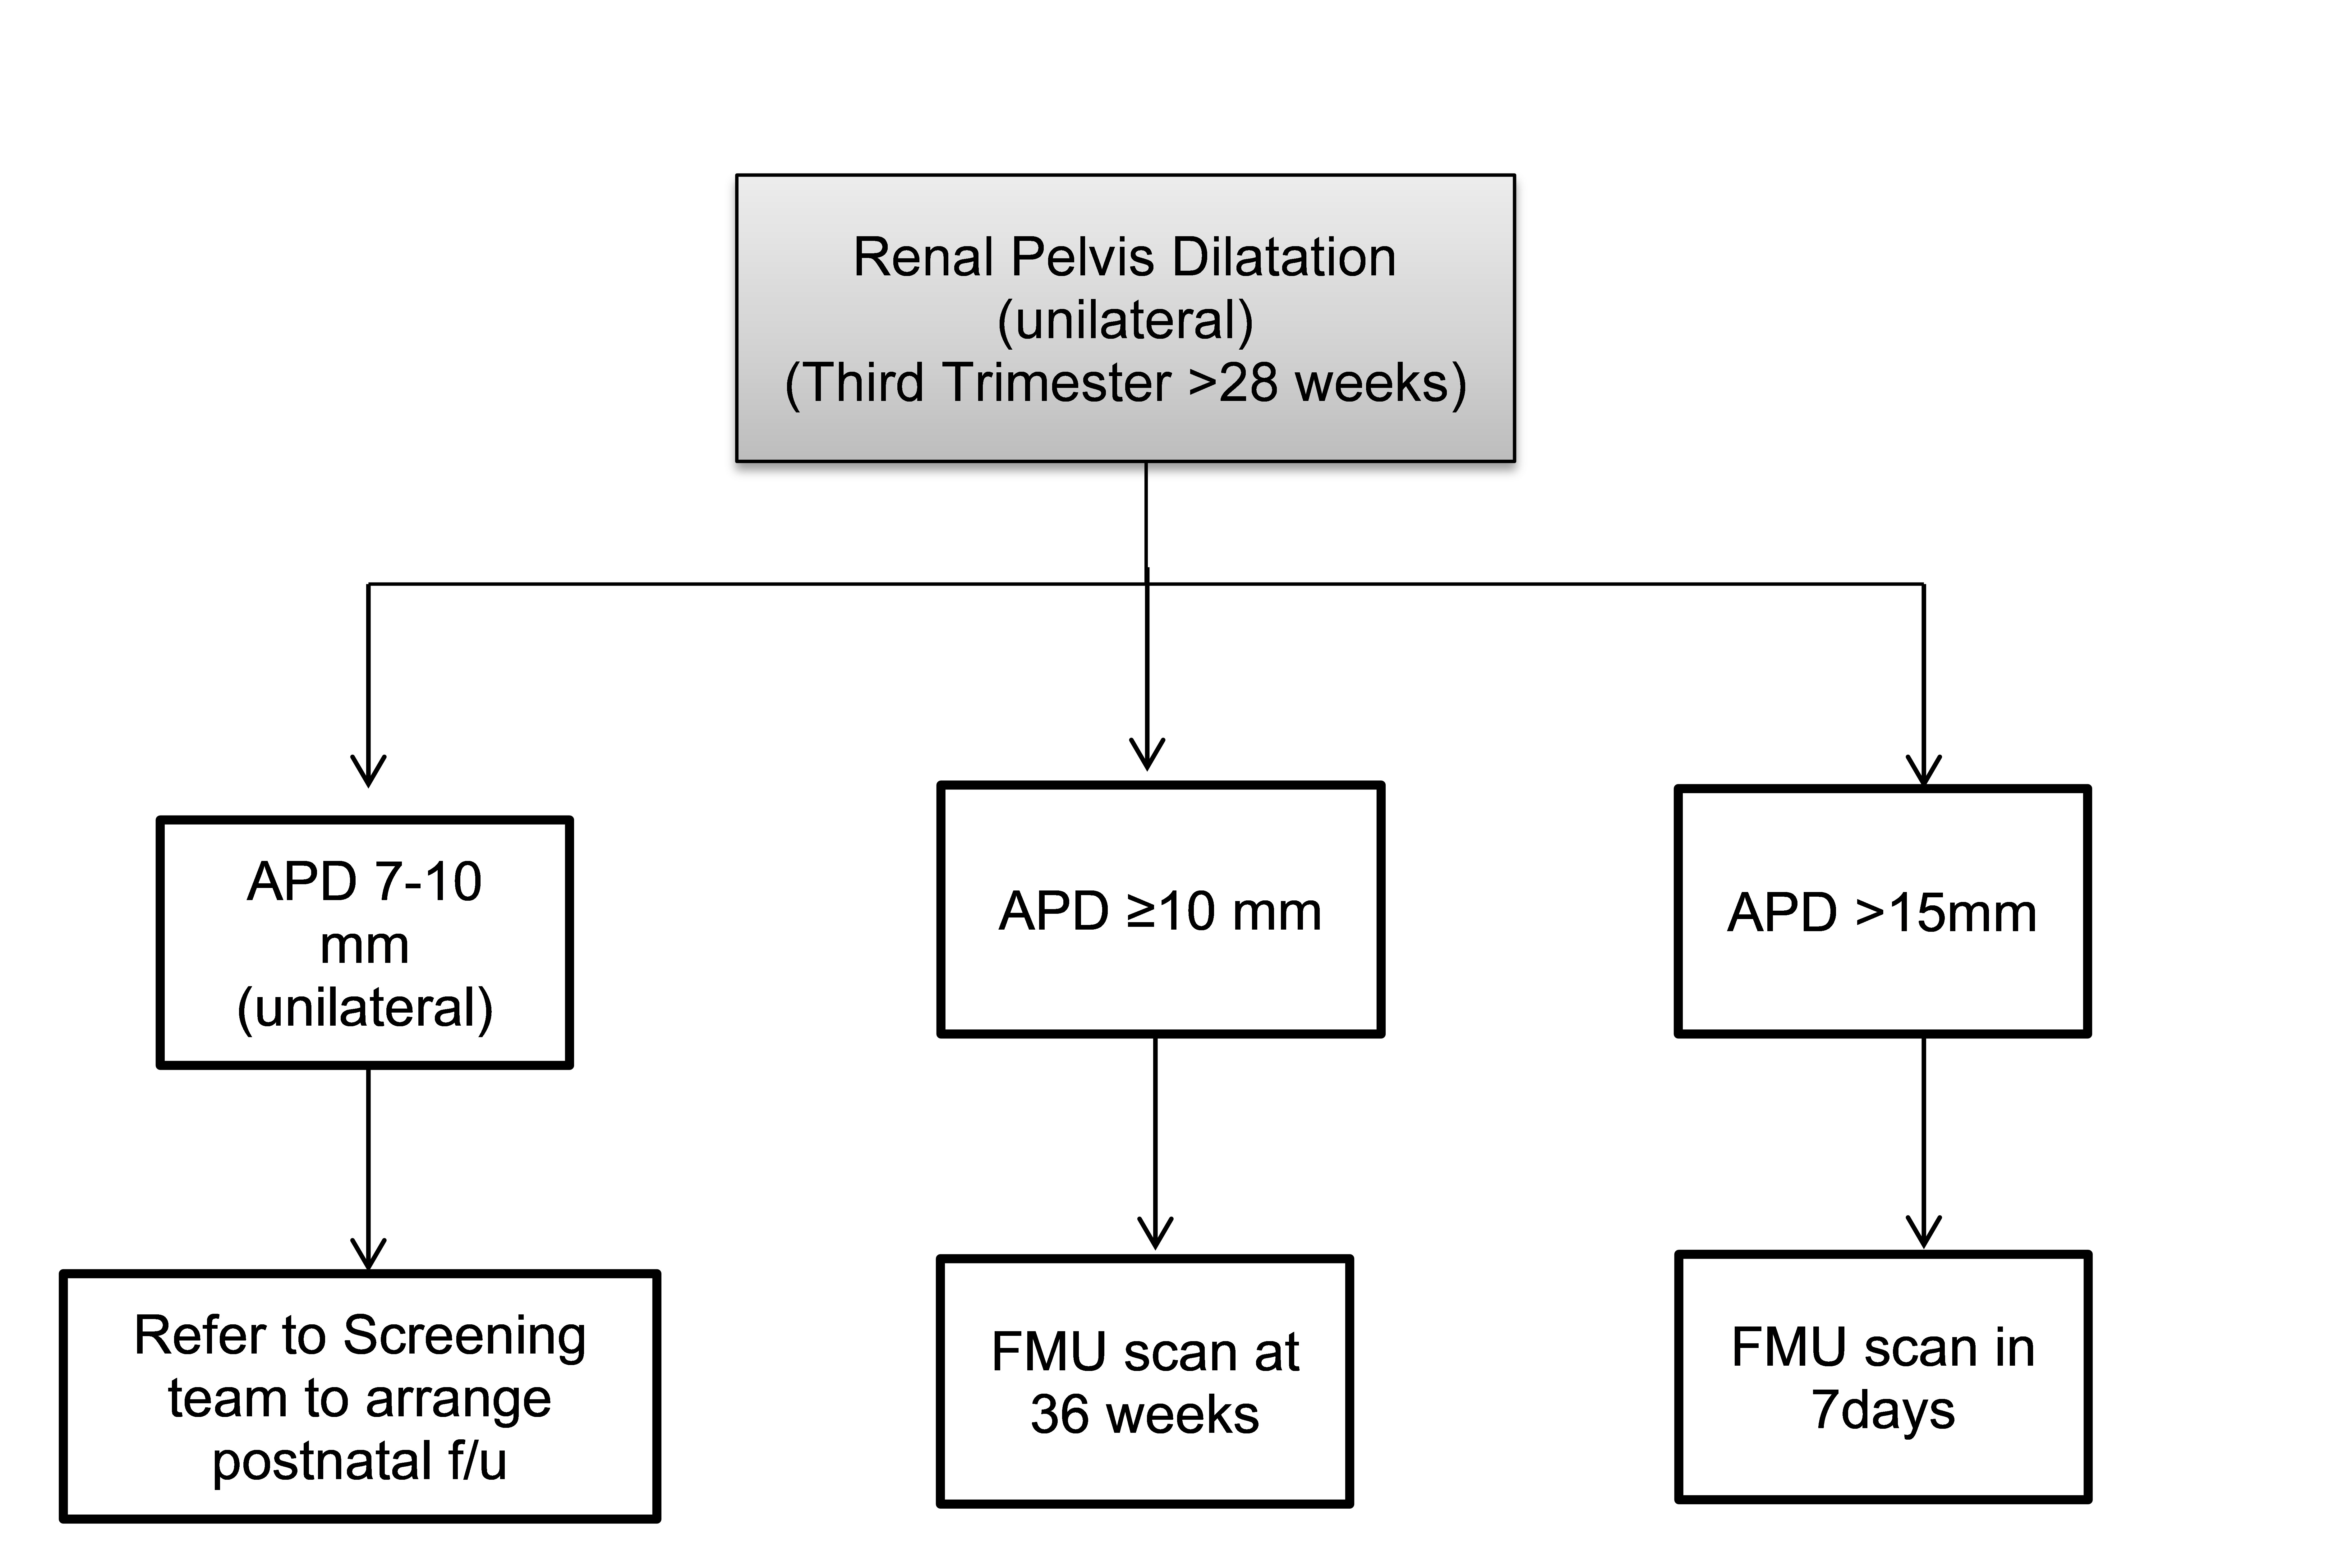
Detection in Third Trimester
-
If moderate hydronephrosis (APD>10mm) is detected, the woman should be referred to Fetal Medicine Unit for review at 36 weeks.
-
If severe hydronephrosis (APD >15mm) is detected, the woman should be reviewed in Fetal Medicine Unit within 7 days. Follow up scan should be arranged every 4 weeks or sooner if indicated. Referral to a tertiary centre if the fetal medicine team feels this is required (Appendix 2).
Cases of moderate and severe hydronephrosis should be discussed with the neonatal team at the antenatal high risk multidisciplinary team (MDT) meeting or equivalent to discuss postnatal management.
Screening team will update the Epic problem list which will generate a fetal problem banner and follow their high-risk process and ensure fetal MDT and fetal chart documentation is completed.
If a meeting with a Paediatrician is deemed necessary in the antenatal period, this will be arranged.
8. Informing women about the anomaly
It is important that the woman is given clear information about what has been found at the ultrasound examination. Initially, the explanation will be given by the sonographer who undertook the scan.
Information should be tailored to the individual and given in a staged, unhurried and sympathetic way. The woman may be upset and may not understand and remember completely what has been told. She should be offered an information leaflet about the finding to read in her own time.
9. Documentation
All scan reports are recorded on the electronic patient record (Epic EPR). The individual plan of care is documented in the antenatal records to reflect the discussions undertaken amongst the multidisciplinary teams. An alert should be entered on the electronic patient record (Epic EPR) in cases of severe hydronephrosis. All referrals are documented in the electronic record (Epic)
10. Postnatal management
After delivery the midwife should inform the neonatal registrar of the antenatal ultrasound results and renal pelvis dilatation.
The baby will have a routine newborn physical examination performed and the antenatal ultrasound scans will be reviewed. Further postnatal investigation and management will then be arranged following review of the postnatal further investigations flow sheet.
The mother should be given an information leaflet if not given antenatally.
All cases of bilateral or severe unilateral dilatation or any of the findings (ureteric dilatation, calyceal dilatation, parenchymal thinning), should be discussed with the duty neonatal consultant prior to discharge.
Further postnatal investigation and management will then be arranged following review of the postnatal further investigations flow sheet.
Male infant with bilateral dilated ureters with thickened bladder and poor urinary stream needs urgent paediatric urology referral and discussion to exclude posterior urethral valves (PUV).
Day 1
-
Measure blood pressure.
-
Check serum creatinine if bilateral.
-
Give mother an information leaflet if not given antenatally.
-
Start Trimethoprim 2 mg/kg nocte, if indicated.
-
Request ultrasound (U/S) “US Urinary Tract” and follow up – timing depending on severity on antenatal scans. Ultrasound scan must be ordered with one of the Paediatric/Neonatal consultants as the authorising clinician, not a midwife or obstetrician.
-
If severe or if moderate in bilateral or solitary kidney: ultrasound before discharge and consultant to review results on the same day.
-
If moderate in unilateral kidney: U/S at 1-2 weeks; the clinical team responsible for the care of the baby should ensure results are reviewed and dealt with.
Postnatal Further investigations Flowsheet
Postnatal management of Antenatally detected hydronephrosis
3rd Trimester measurements – Renal Pelvis dilatation (RPD
11. Further paediatric management
Give Safety Netting advice when discharging baby: describe signs of evolving UTI
Safety netting advice for any baby with RPD and/or at risk of developing infection: Signs that a baby may be unwell include:
-
Difficulty with or fast breathing
-
Poor feeding
-
Not waking for feeds
-
Abnormal drowsiness or irritability
-
Change in skin colour (pale, blue, mottled)
-
High or low temperature
-
Abnormally swollen tummy
If worsening dilatation do a MAG3 (if not done) and discuss with Paediatric Urology.
For stable dilatation, repeat renal USS at 3 months, 6 months and 12 months and discuss with Paediatric Urology.
For recurrent urinary tract infection (UTI) or haematuria – reconsider need for further investigations. Follow NICE guidelines for management of UTI.
Trimethoprim should be continued until the age of 1 year particularly for upper tract dilatation.
For proven vesicoureteric reflux (VUR), continue trimethoprim until out of nappies and passing urine in a good stream.
Family history of vesicoureteric reflux (VUR) in first degree relative
Arrange U/S even if antenatal scans normal as reflux is often autosomal dominant.
Other renal anomalies
Multicystic dysplastic kidney may also be dominant and asymptomatic.
12. Implementation plan
This guideline will be implemented as follows:
Guidelines are approved at Obstetric Clinical Governance Group (OCGG) and Paediatric Clinical Governance, the minutes of which are available on the maternity shared drive.
After approval and ratification by the Clinical Governance groups, the guideline will be placed on the guidelines platform for viewing by any member of staff.
13. Monitoring Compliance of Guideline
Data will be collected by auditing the maternity and neonatal notes on an annual basis and presented in a recognised forum.
A Risk Summit is performed quarterly by the screening midwives in order to ascertain the woman’s opinion of her care. This includes eliciting whether the information given was of sufficient depth and in an appropriate format for her to make an informed decision regarding the future of her pregnancy. The Risk Summit entails a telephone conversation between the woman and a screening midwife after discharge from maternity care, usually when the baby is one or two months old.
In addition to the risk summit, documentation in the maternity notes is audited as part of the regular records audit (see Maternity Services Record Keeping guideline).
Appendix 1 - Caliectasis (calyceal dilatation), cortical thinning, hydroureter, bilateral RPD, dilated and thick walled bladder (≥2mm)and/or urethra: referral to FMU (Second trimester)
Appendix 2 - Caliectasis (calyceal dilatation), cortical thinning, hydroureter, bilateral RPD, dilated and thick walled bladder (≥2mm)and/or urethra: referral to FMU (Third trimester)